
The panels at work
A medical document travels the pipeline: term binding → service act → dispute → reconciliation. The four panels are the four workplaces where disputed items go to a human for authorization, and the product makes that decision fast, specific and defensible.
Below is how the work goes at each step, in pipeline order: who works there, what arrives at the panel and what leaves it for the next step, and the working screen of that step. Under each screen sit its fork screens — the second layer of logic for that pipeline step. They open in one action: a click on the link. The screens themselves are English translations of the authorized Russian workplaces.
Step 1. Binding panel: disputed term recognition
Who works here: clinical coders; the physician — for clinically significant bindings.
What reaches this panel is what the pipeline recognized but has no right to decide: equally strong semantic-search candidates, terms missing from the vocabulary. The operator sees the source fragment, the ranked candidates and their definitions — and authorizes the choice. Automation has stopped: the term has several similar candidates, and the final choice is made by a human. The decision is recorded with its author and the descriptor version. What leaves the panel: bound terms go on to the act, missing ones become vocabulary-extension candidates.
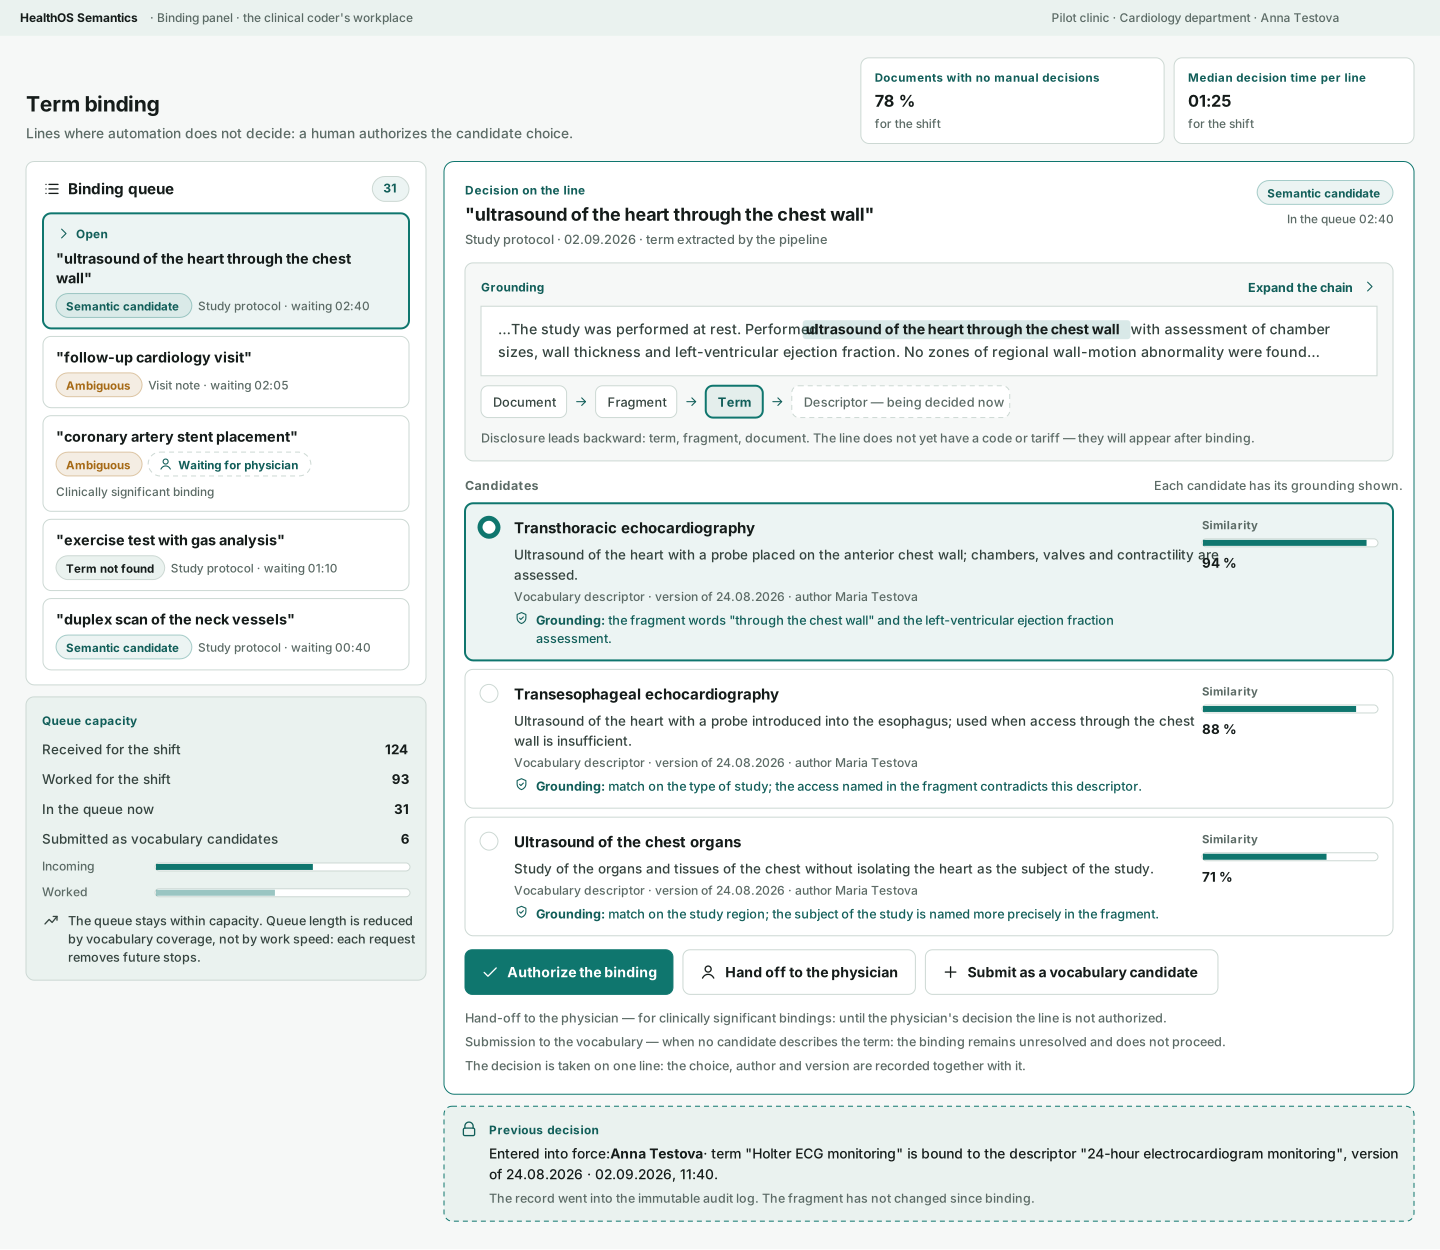
The workplace is wider than the window: the frame scrolls sideways.
Term binding: empty · index lagging · queue growing
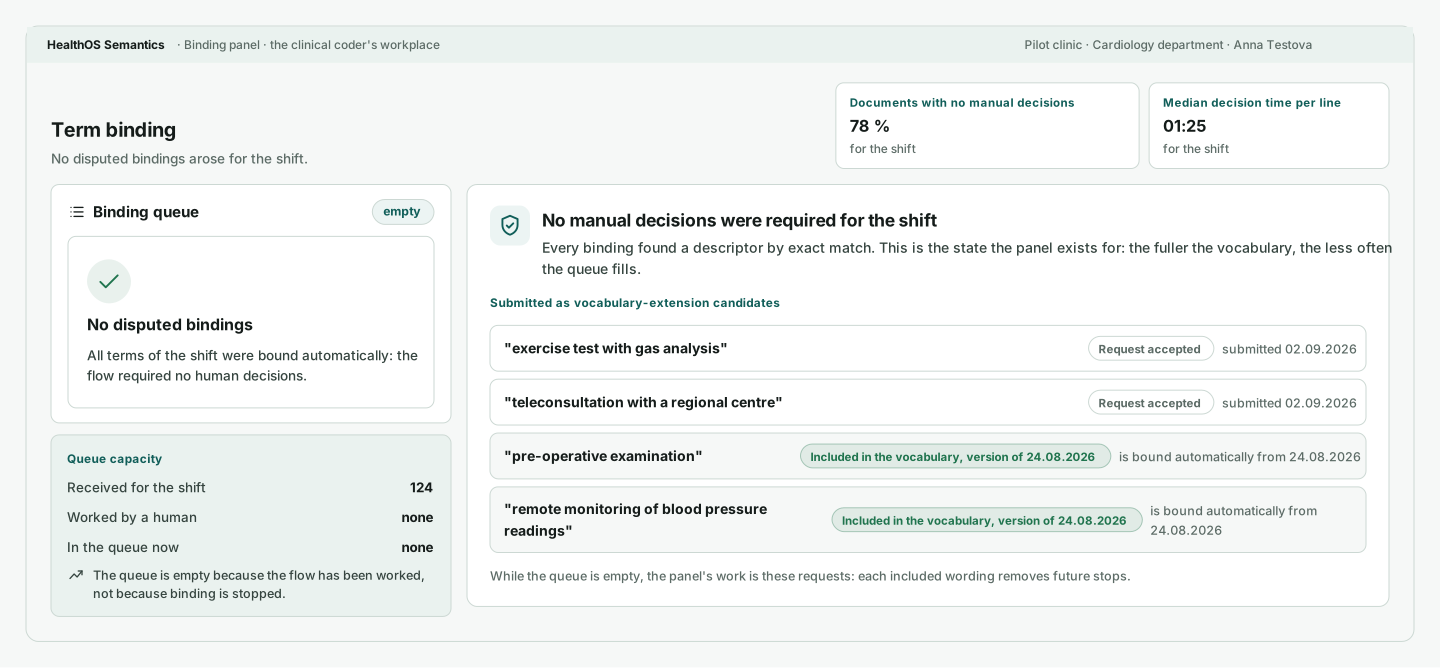
The frame scrolls sideways.
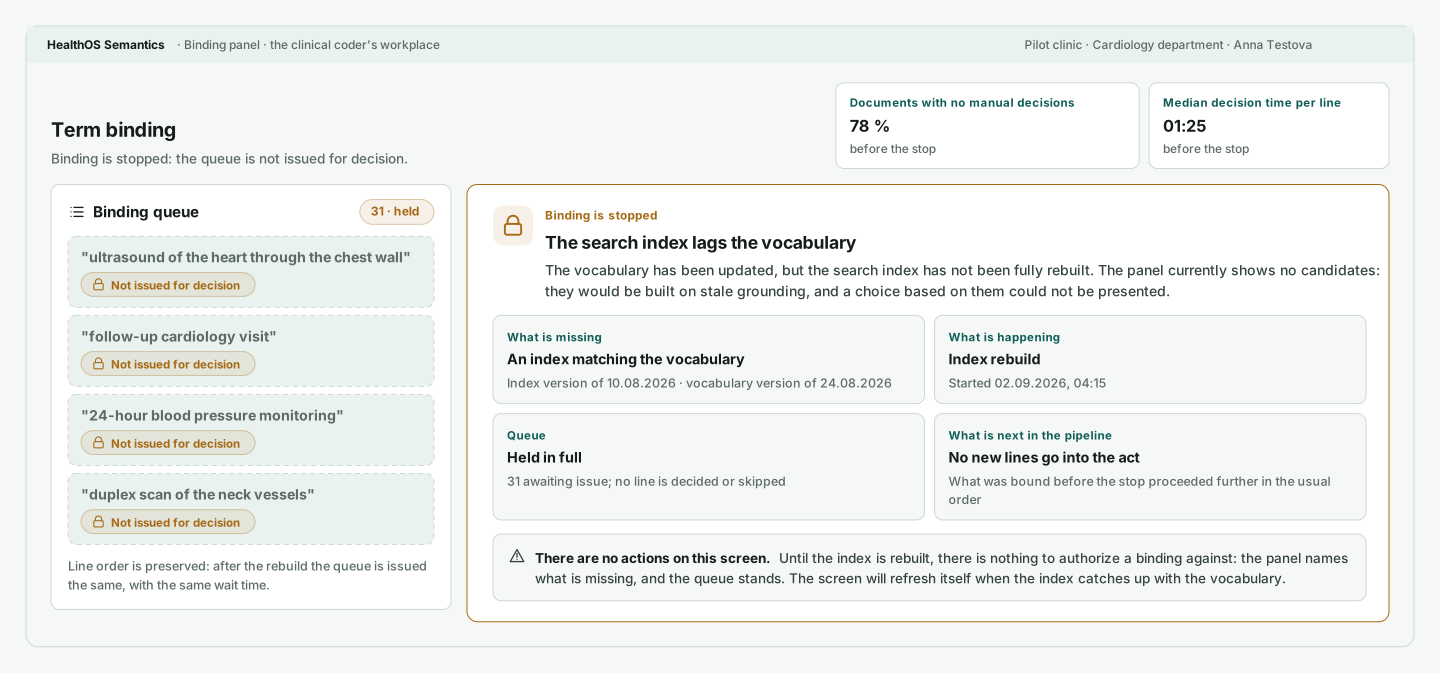
The frame scrolls sideways.
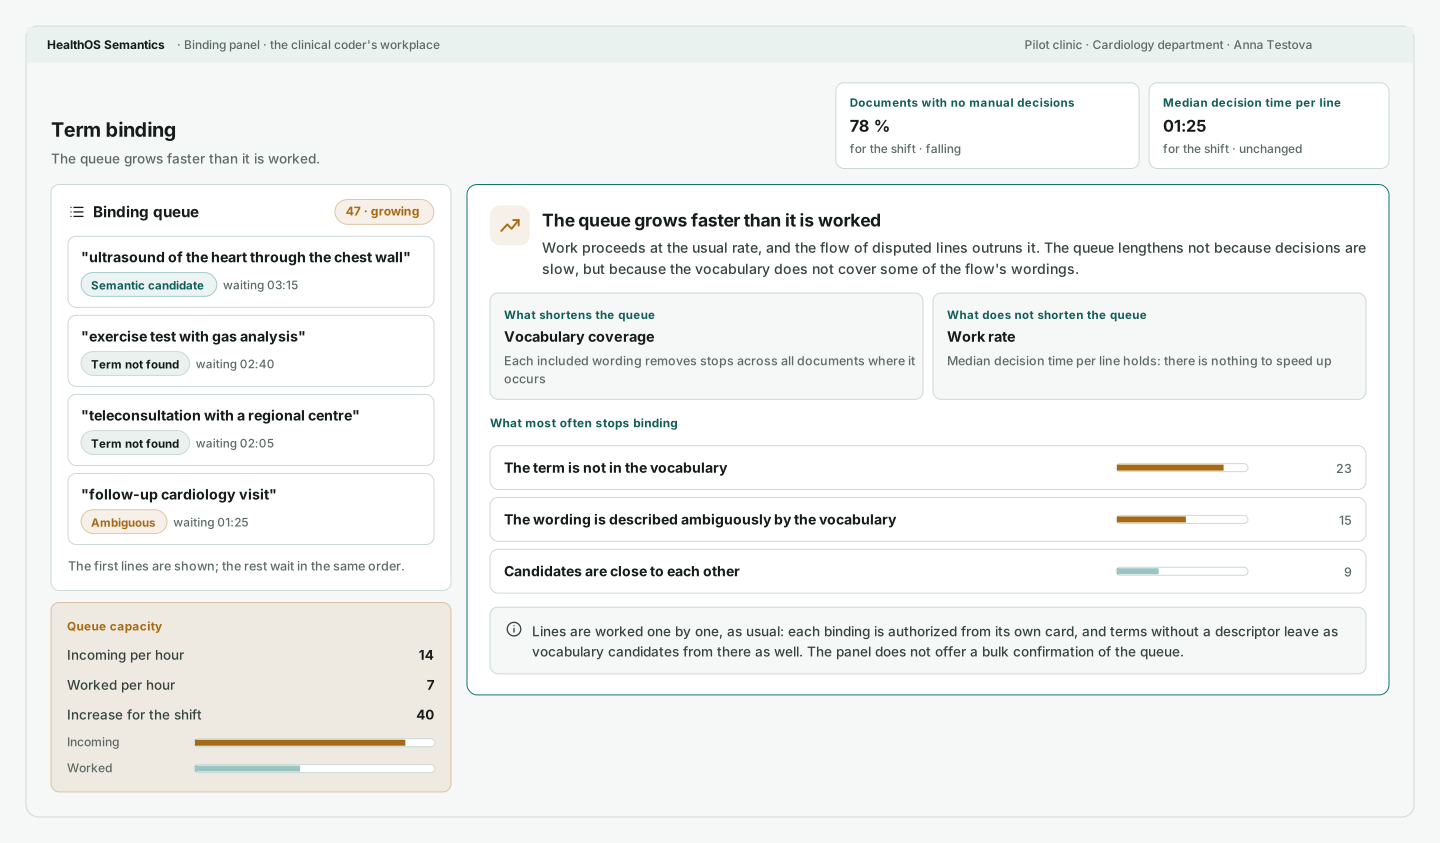
The frame scrolls sideways.
- A choice between grounded candidates instead of reading the whole document.
- Higher throughput without higher risk: every decision is recorded and grounded.
- Every confirmation improves future coverage — the automatic-binding share grows.
Metric: share of documents needing no manual decisions; median decision time per line.
Boundary: queue growth beyond operator capacity is a signal to improve vocabulary coverage, not to rush the operators; the panel shows this metric explicitly.
Step 2. Act panel: disputed act lines
Who works here: the billing office; the department head — for lines with clinical content.
Bound terms are assembled into the service act, and everything that does not assemble silently lands on this panel: a service without a reliable binding to the document, an ambiguous tariff, a mismatch between what is billed and the medical document. Such lines do not enter the act — fail-safe by principle. The operator works the line next to its grounding; lines with clinical content go to the department head. What leaves the panel: an act in which the disputed part has already been removed.
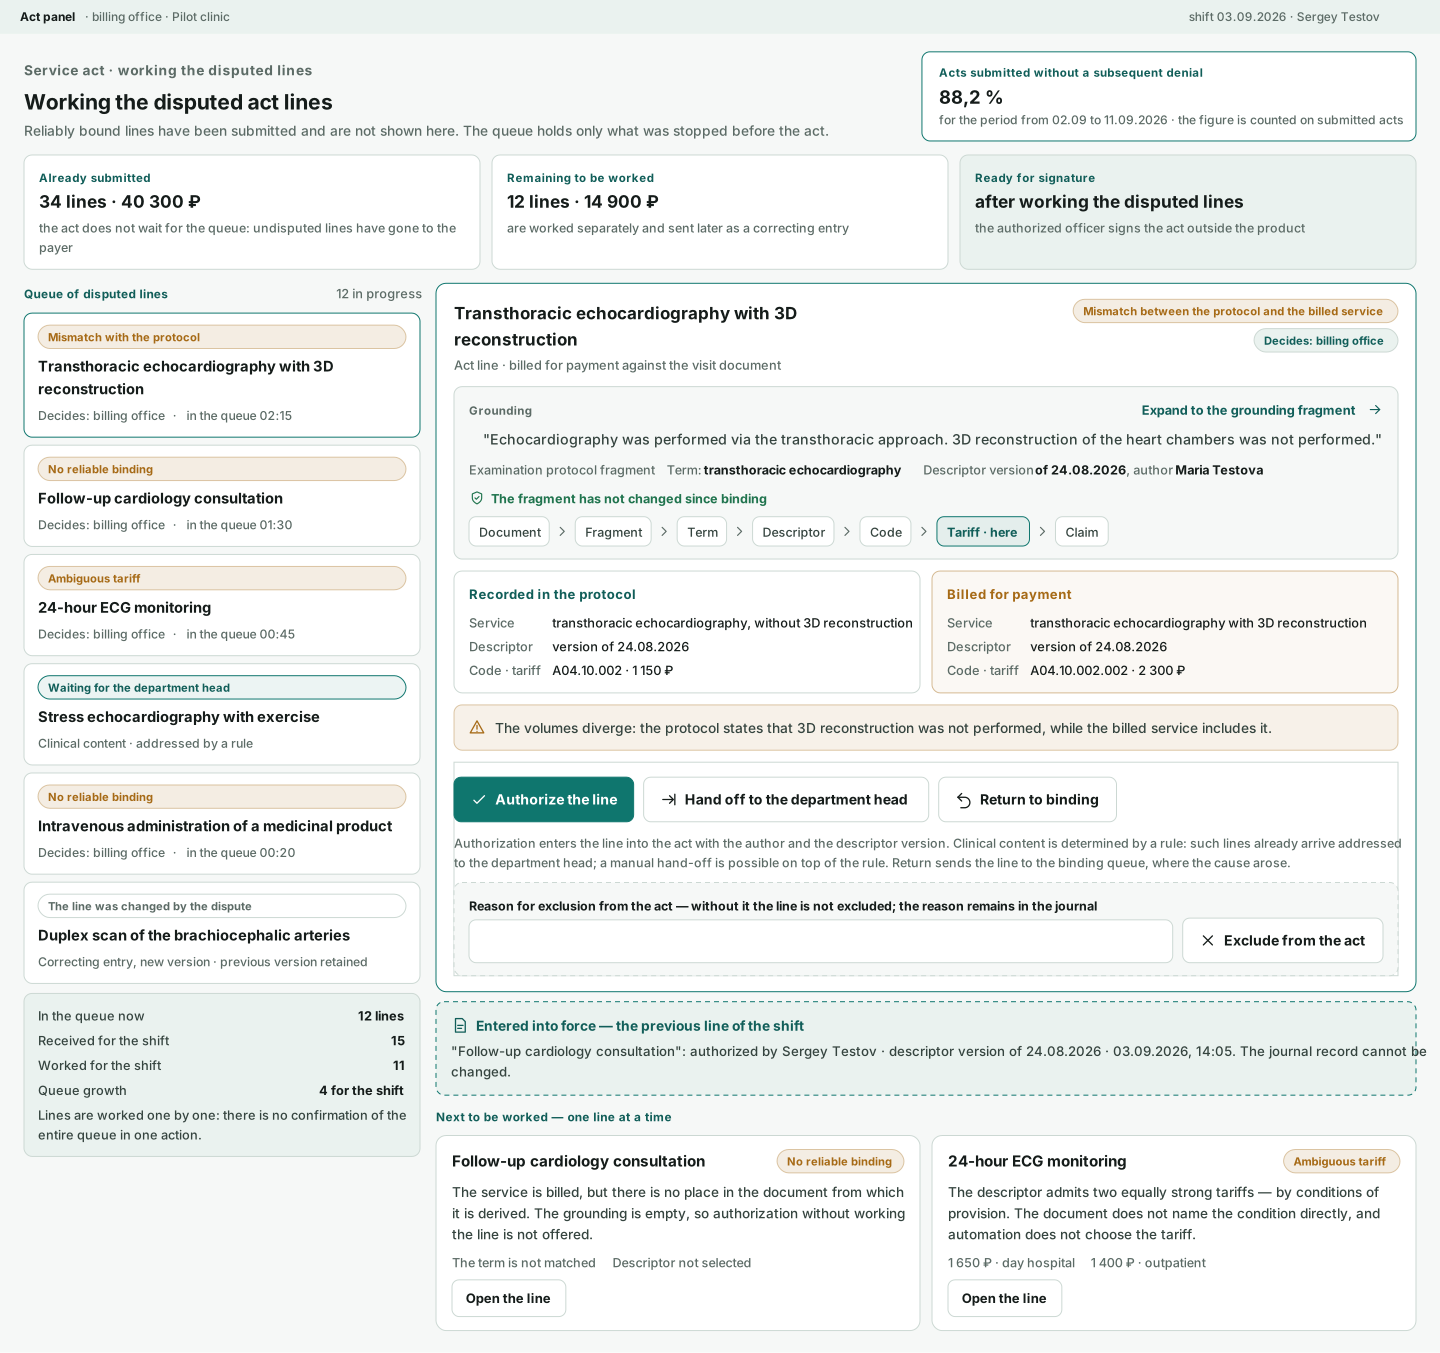
The workplace is wider than the window: the frame scrolls sideways.
Working the disputed act lines: empty · stopped upstream · waiting for the department head
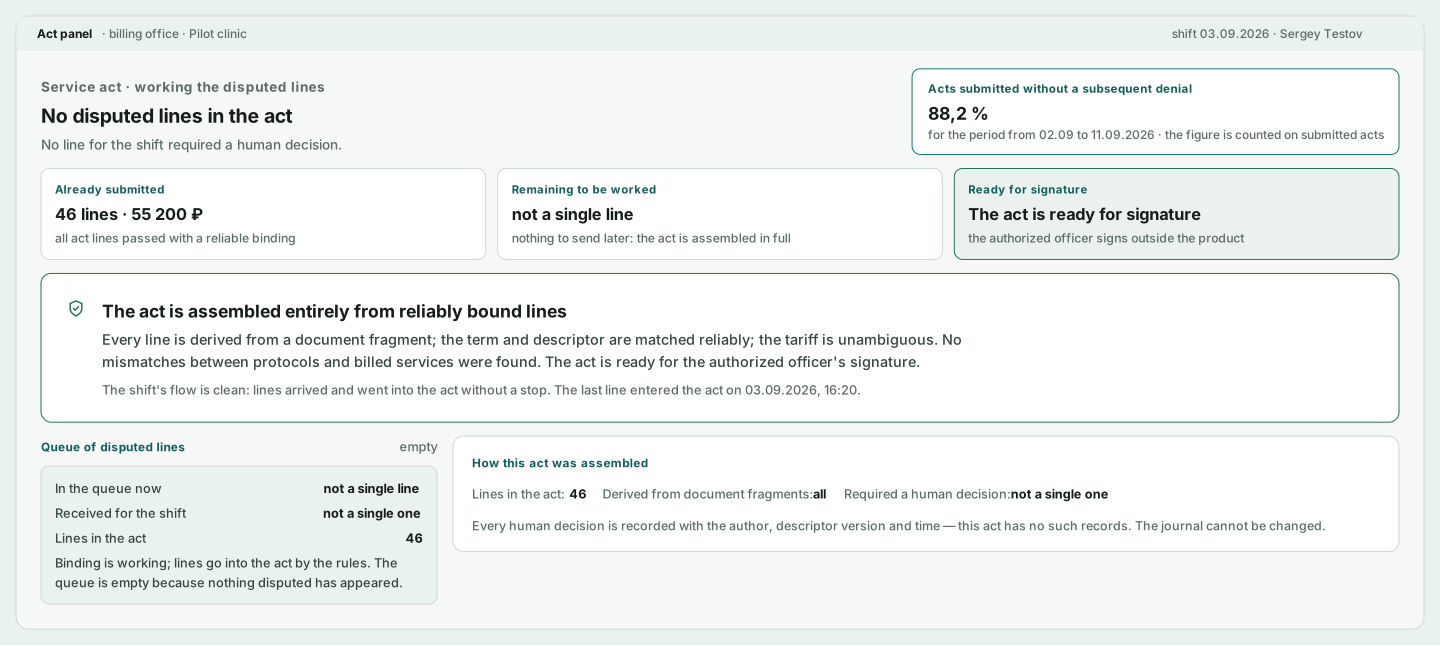
The frame scrolls sideways.
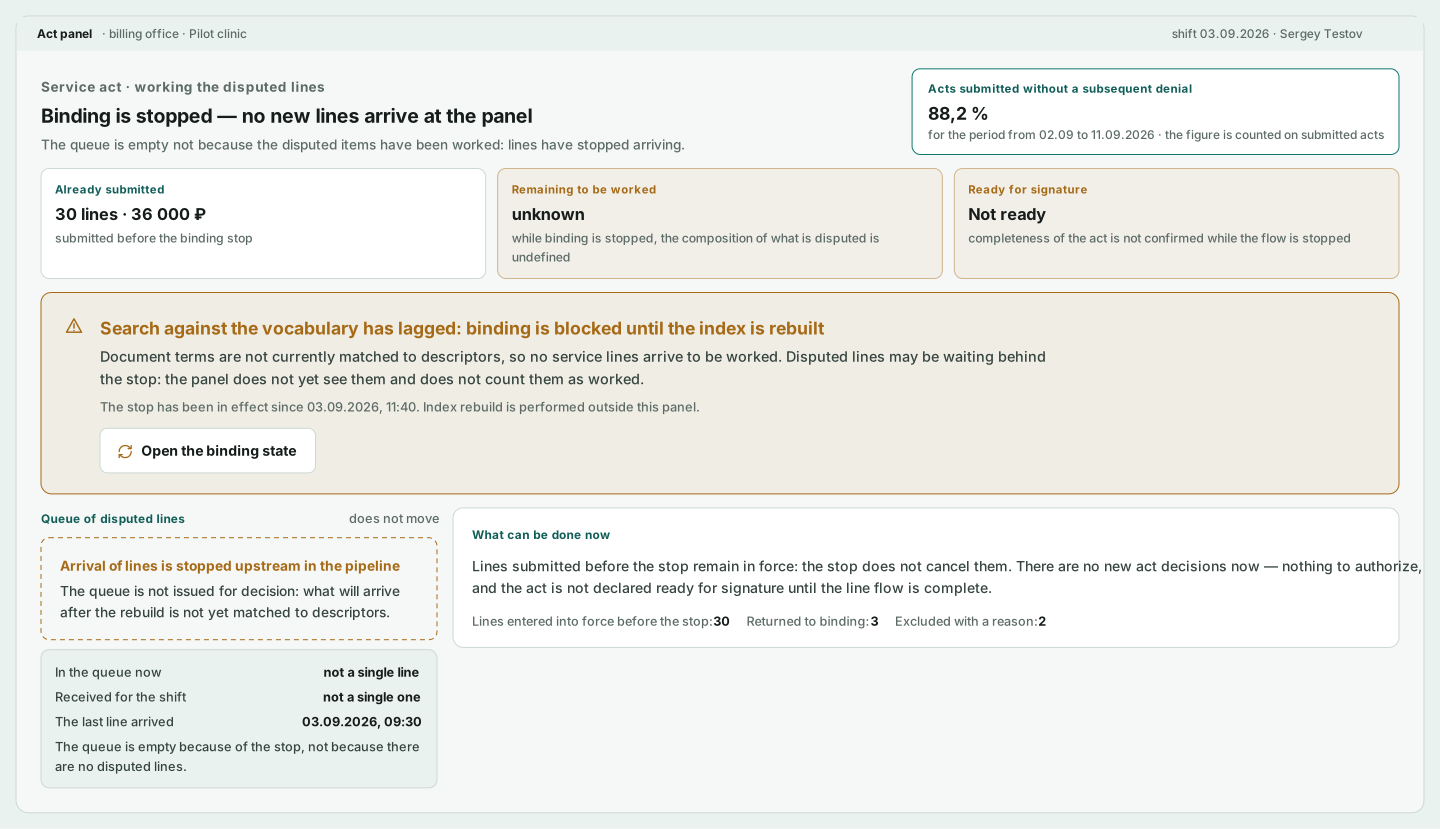
The frame scrolls sideways.
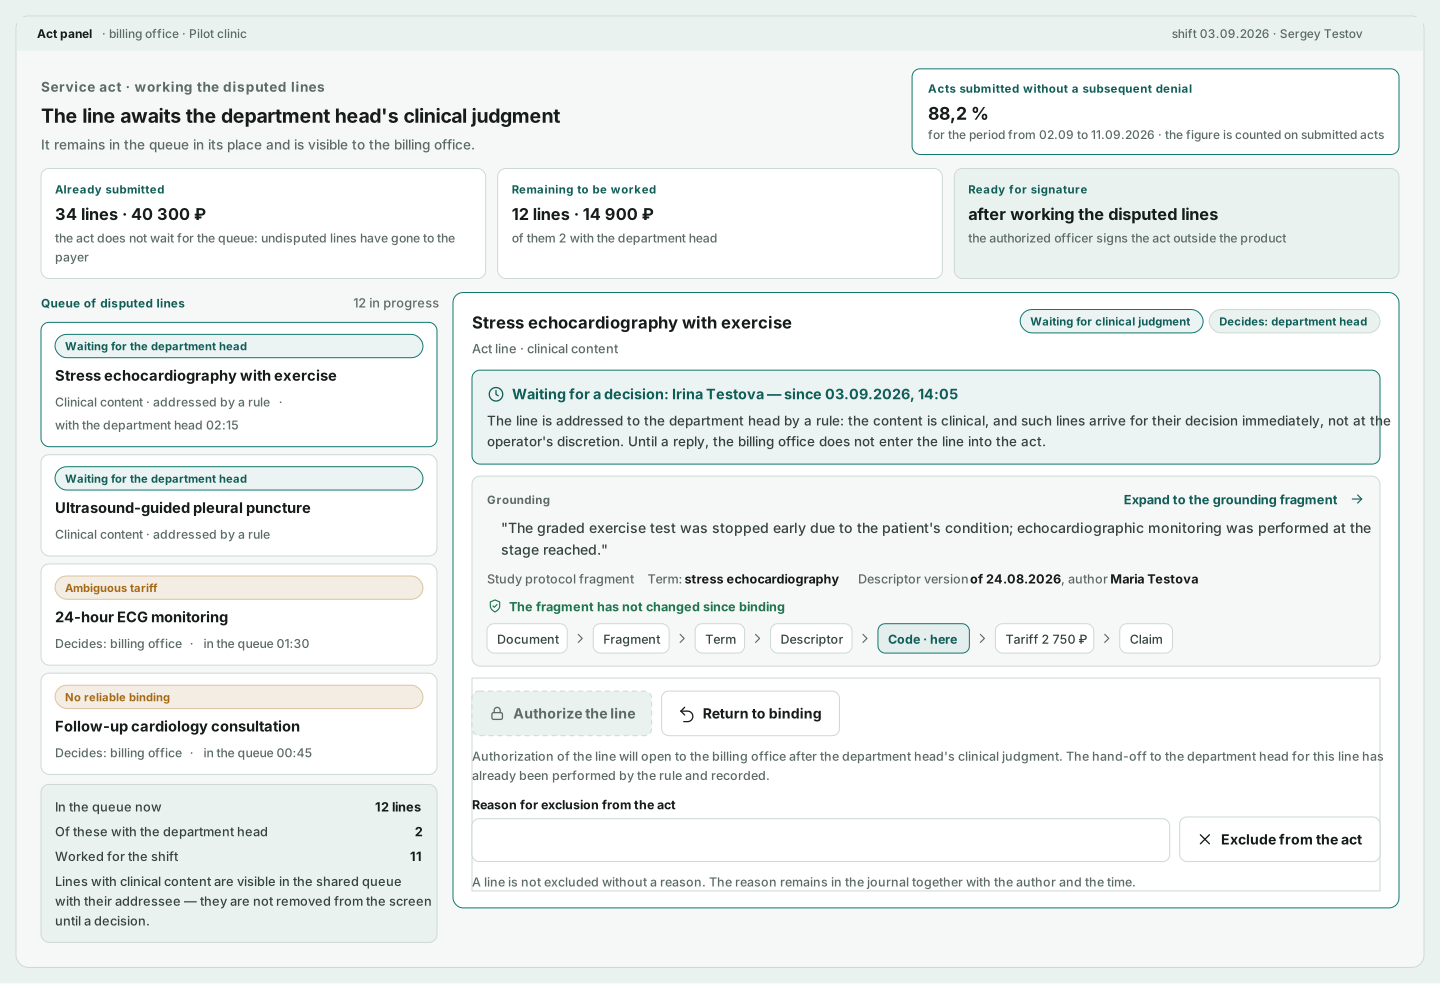
The frame scrolls sideways.
- An act that will not bounce: disputes surfaced and resolved before submission.
- Work in the cheap “before the claim” phase instead of the expensive “after the denial” one.
- Clinical and financial pictures agree by construction.
Metric: share of acts submitted without a subsequent denial.
Boundary: signing the act is a human action outside the product; the panel prepares the decision for the signer, not the signature.
Step 3. Dispute panel: working a denial
Who works here: billing-office dispute specialists; legal — for escalations.
The payer has denied a line — and the work starts not from correspondence but from the history of that line, already assembled. For every denied line the panel shows the payer’s reason, the full transformation chain, the history of decisions made on the binding and act panels, and the pipeline’s recommendation: contest with evidence, correct, or write off. The decision is human. What leaves the panel: a contested line goes to reconciliation, where both sides will see it.
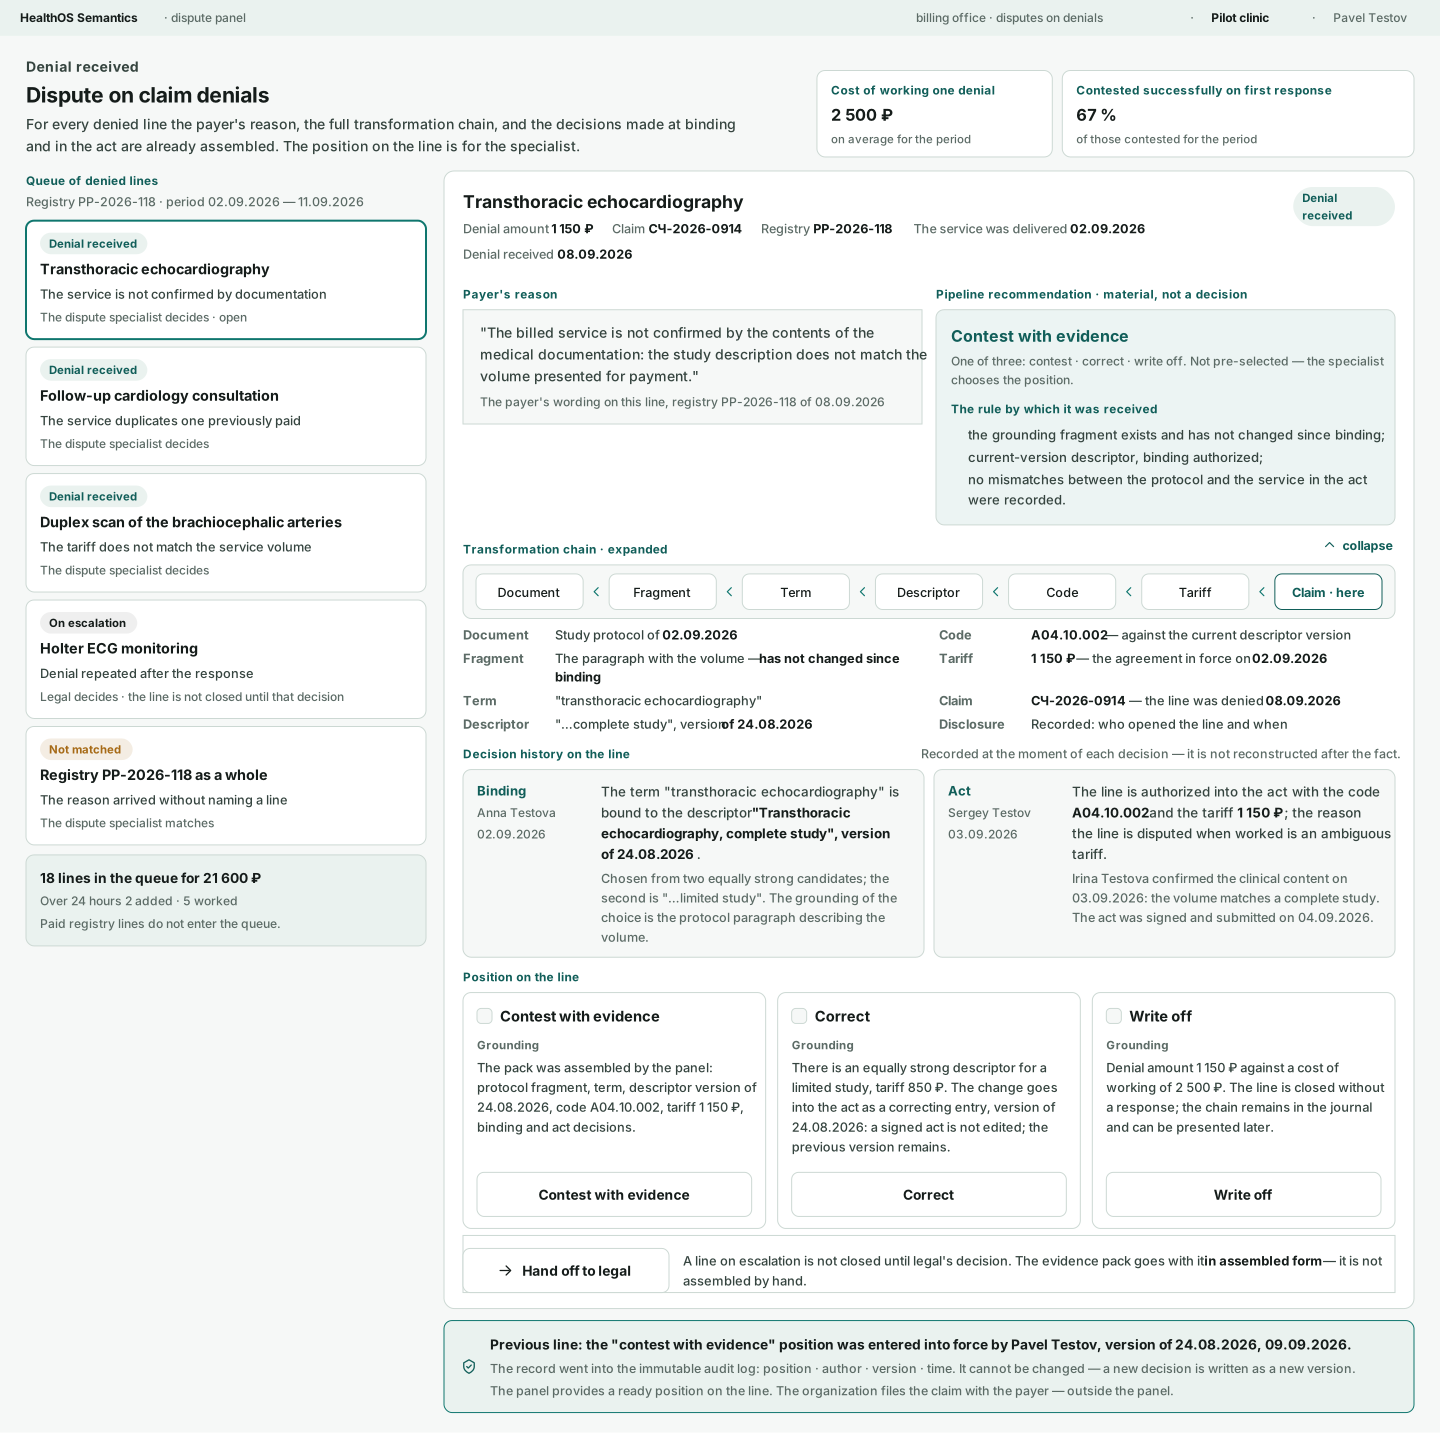
The workplace is wider than the window: the frame scrolls sideways.
Dispute: empty · escalation · not matched
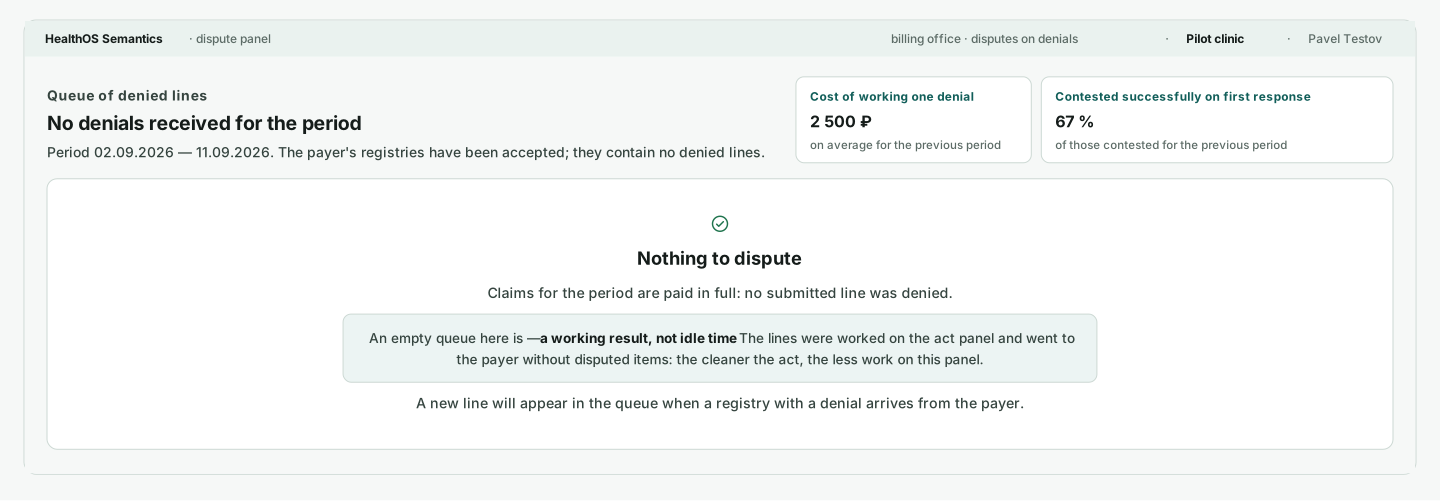
The frame scrolls sideways.
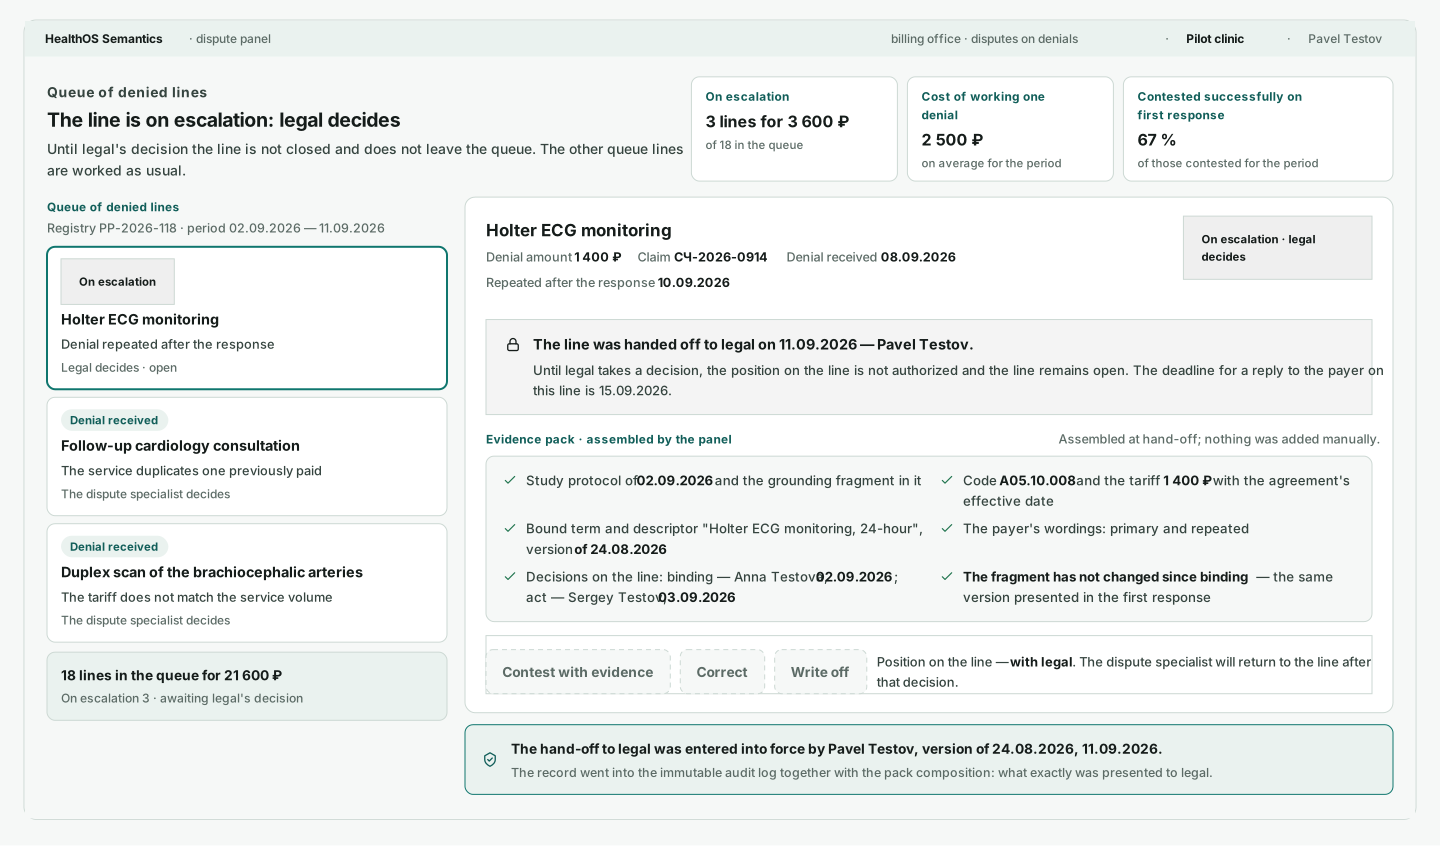
The frame scrolls sideways.
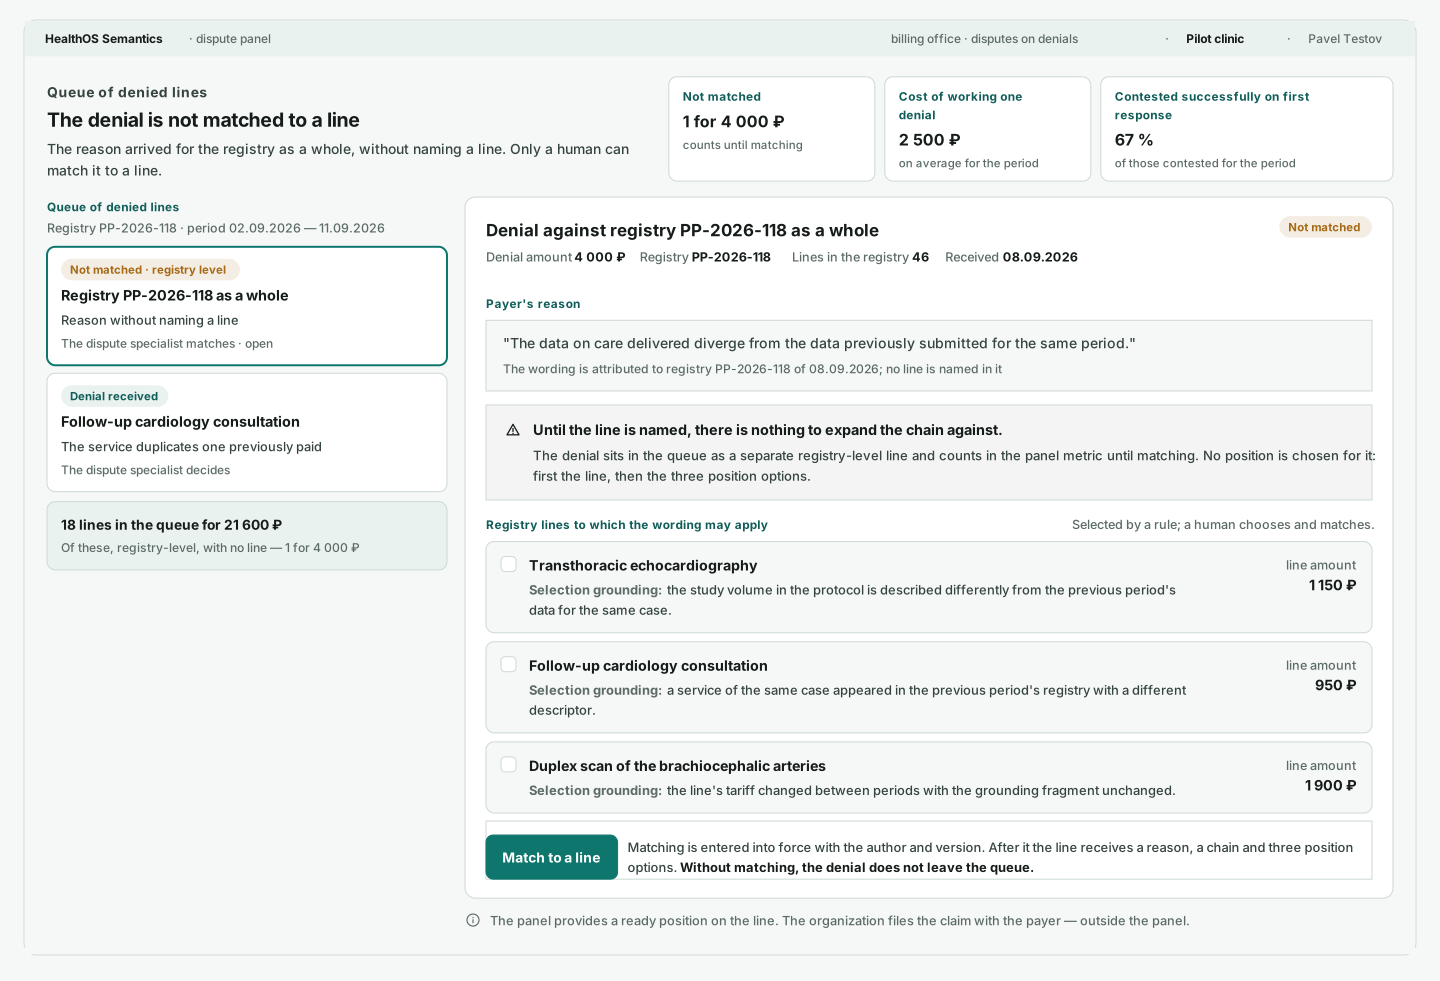
The frame scrolls sideways.
- A denial position in minutes instead of hours: the line history is already assembled.
- A ready evidence pack for escalation — no manual assembly.
- Faster recovery of the denials that do get paid in the end.
Metric: cost of working one denial; share of denials contested successfully on the first response.
Step 4. Reconciliation panel: joint resolution with the insurer
Who works here: the insurer’s expert and the clinic’s representative.
The dispute has reached joint working, and both sides work on one screen: for every contested line they see the same transformation chain — the source fragment in the minimum necessary scope, the bound term, the descriptor with its version and author, the code, the tariff. The subject of reconciliation is evidence of care delivered, not opinions. The per-line decision is recorded, and the dispute does not reopen.
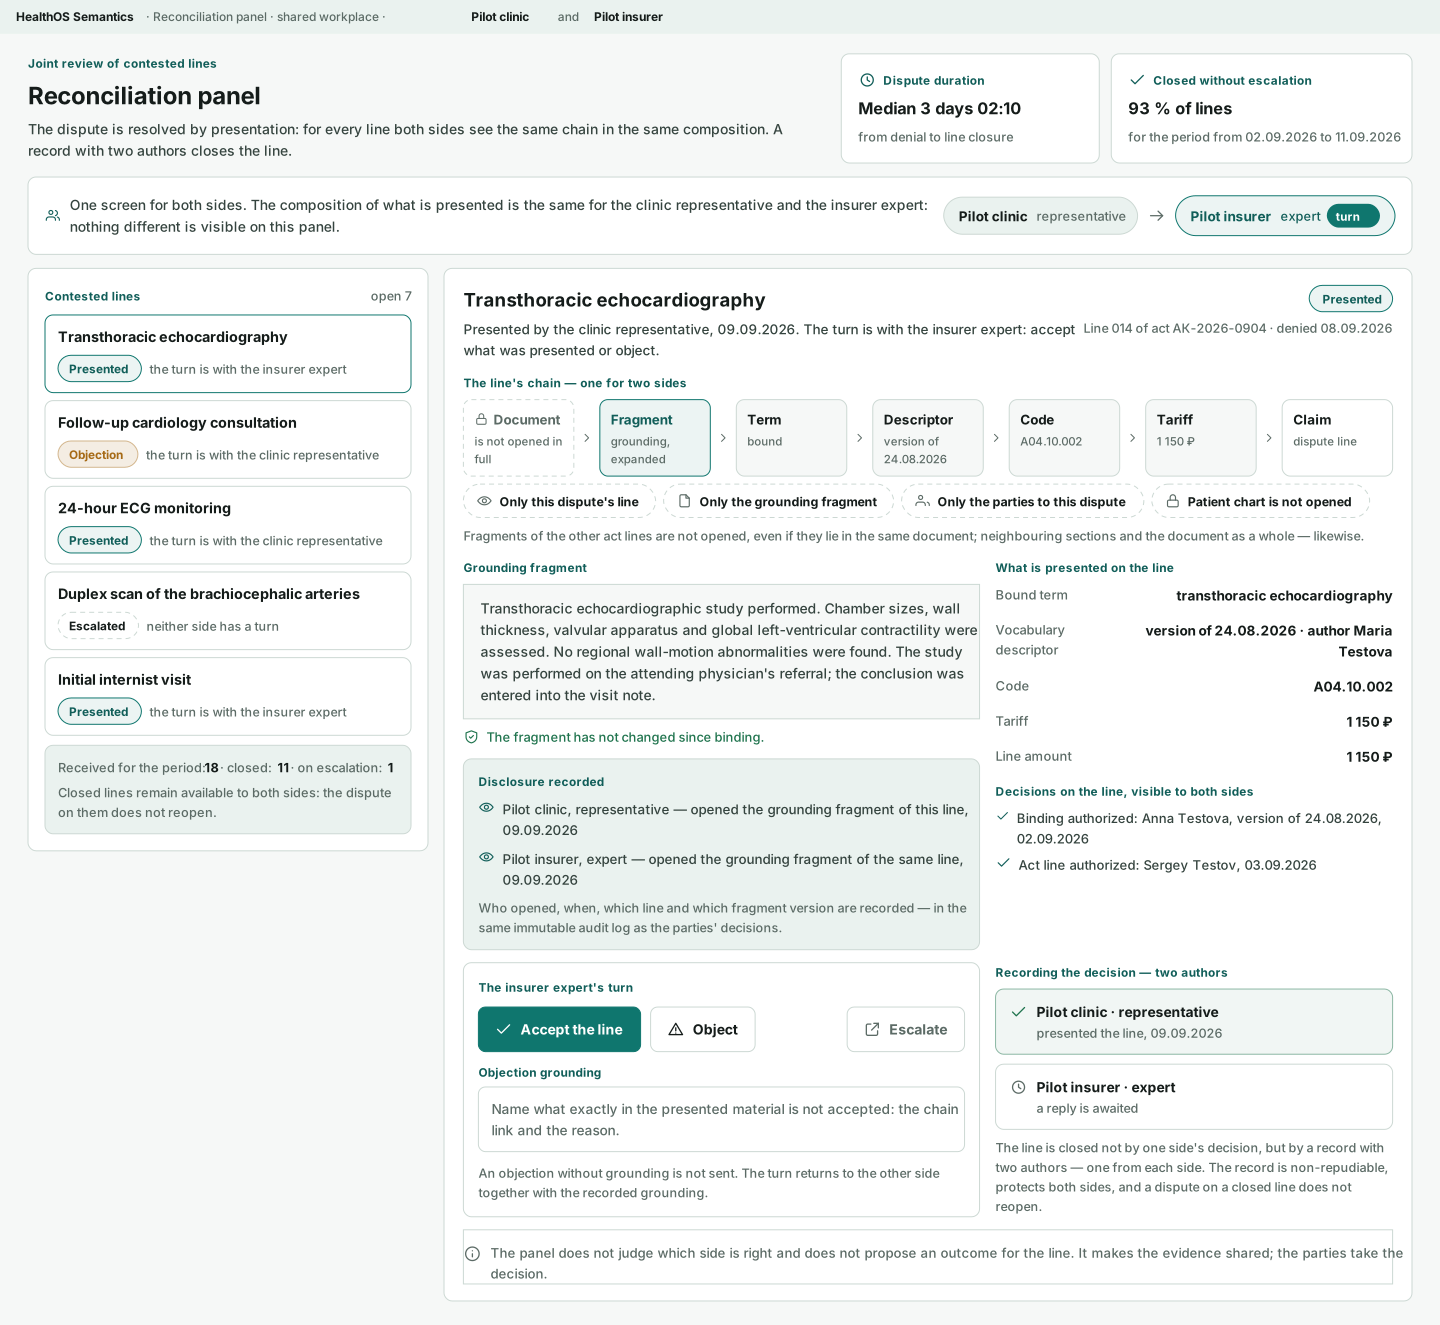
The workplace is wider than the window: the frame scrolls sideways.
Reconciliation panel: empty · not presentable · escalation
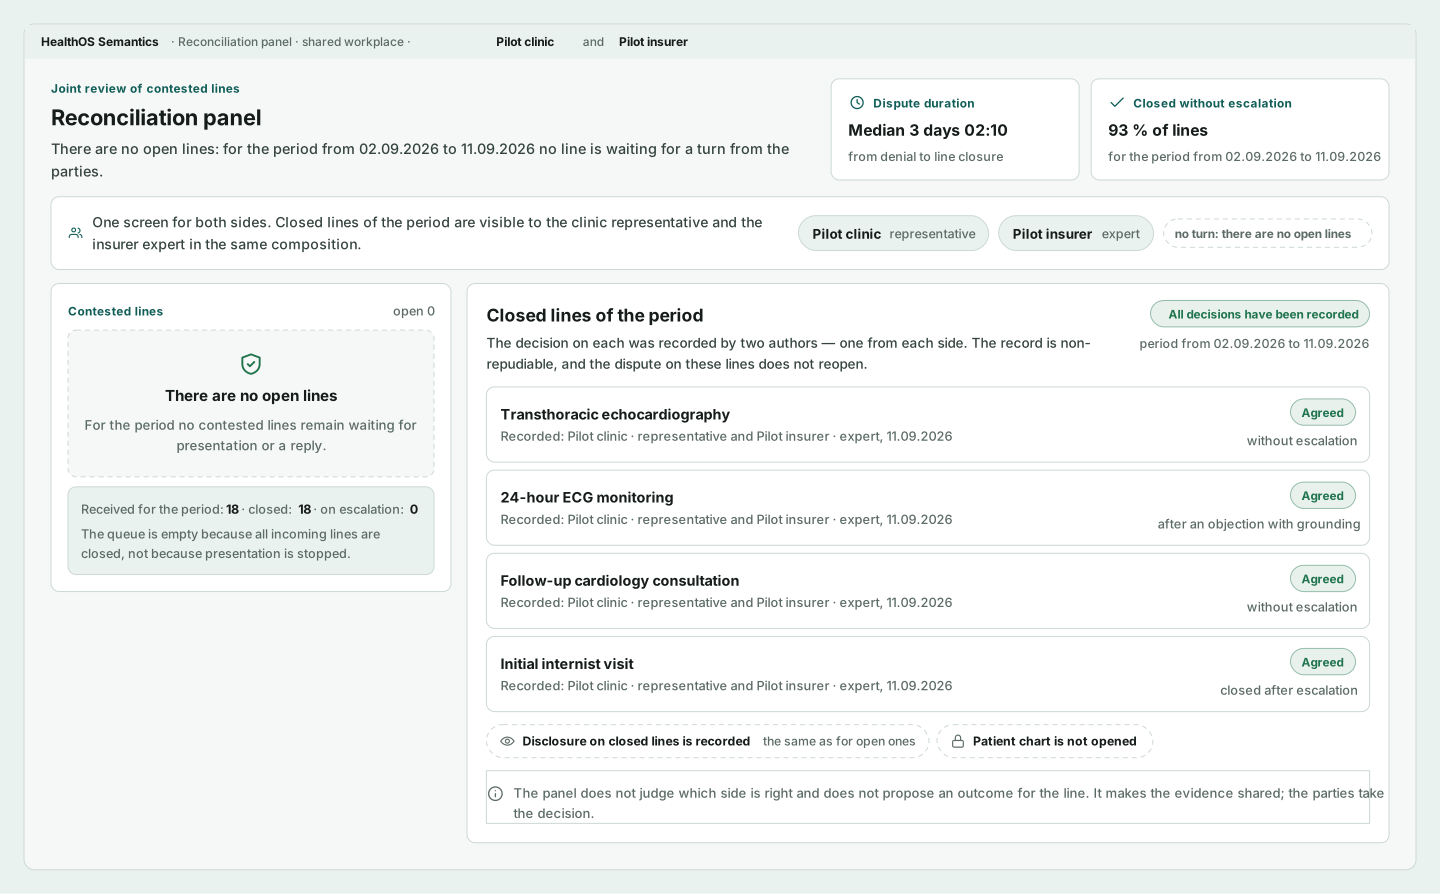
The frame scrolls sideways.
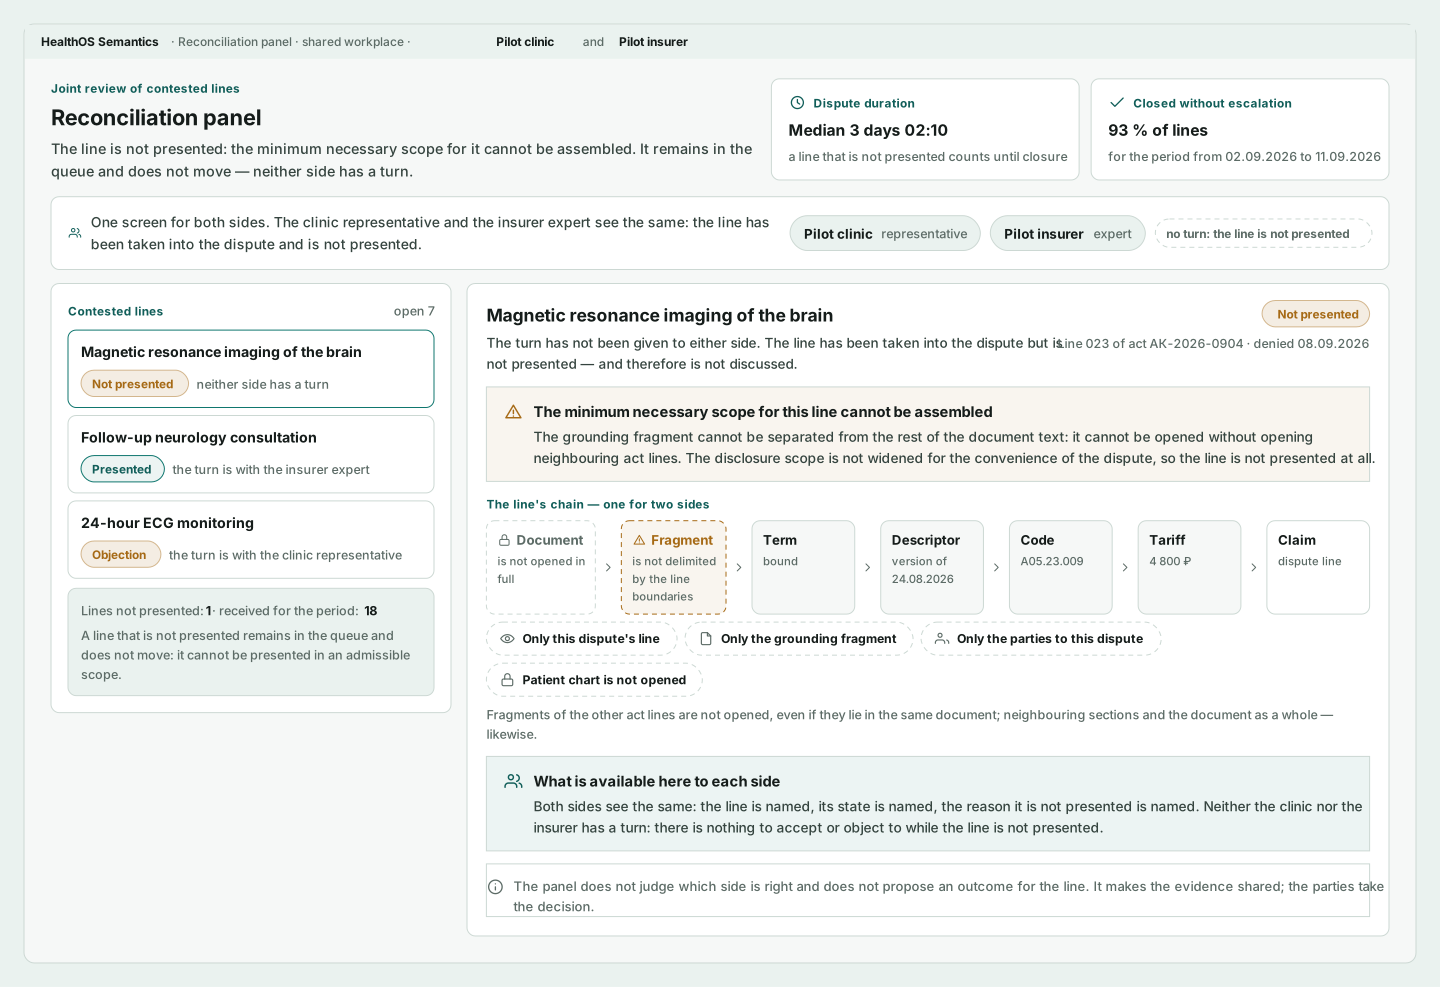
The frame scrolls sideways.
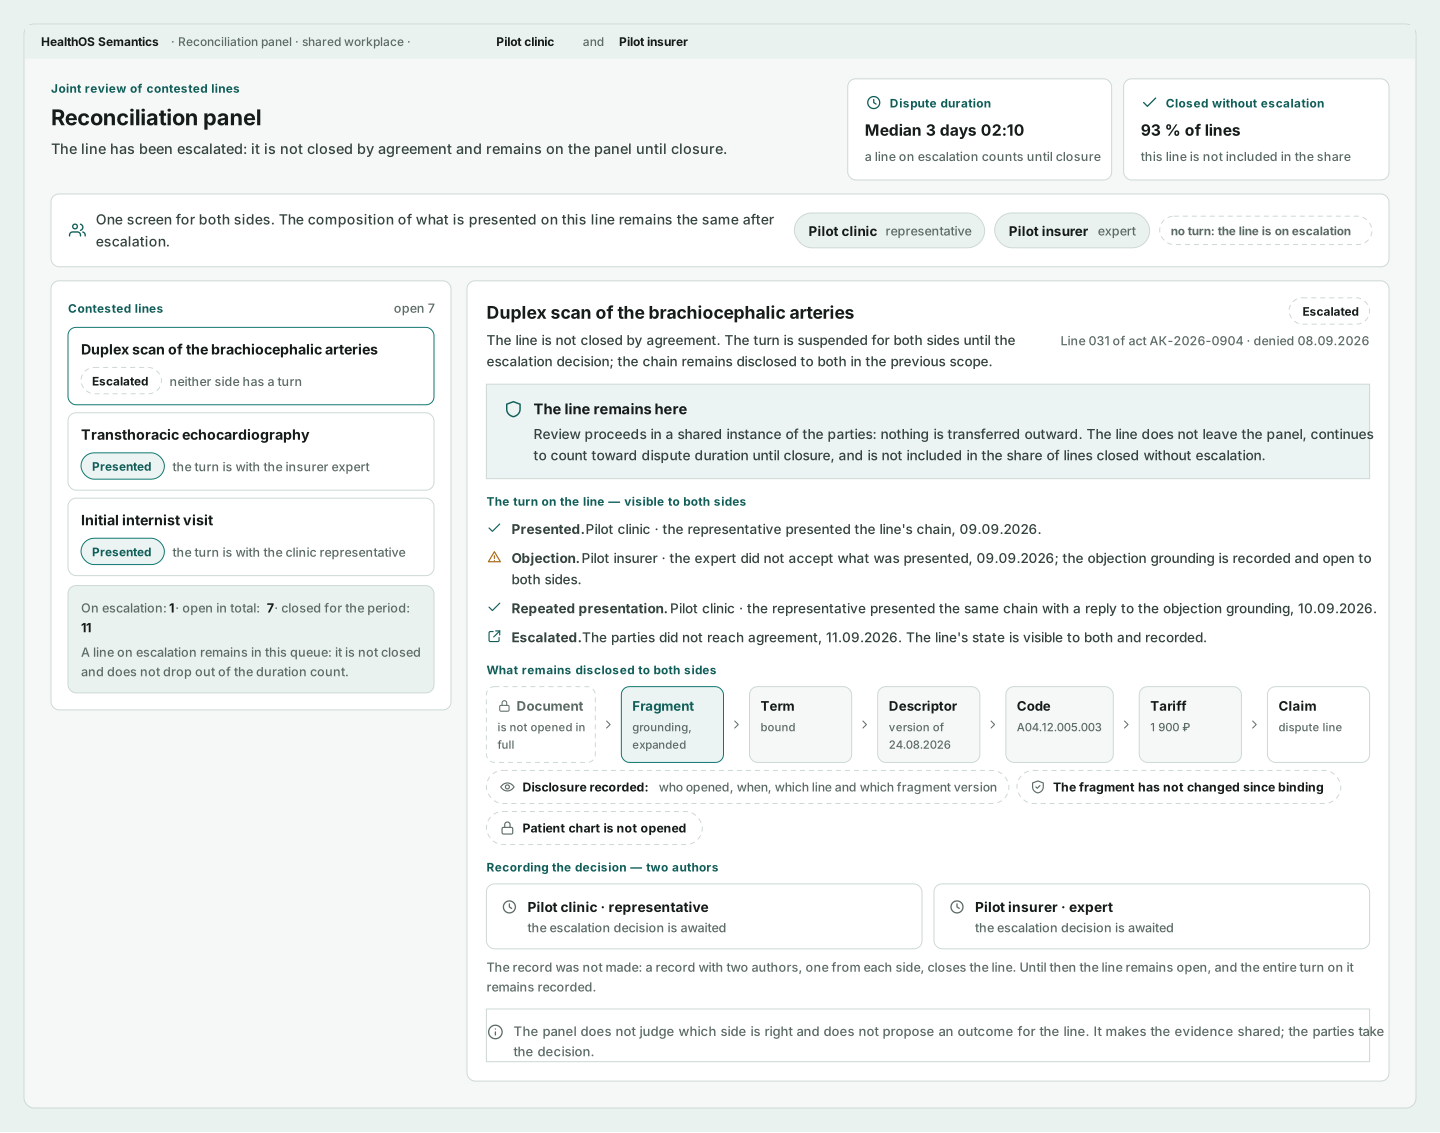
The frame scrolls sideways.
- Disputes resolved by presentation, not by correspondence.
- Per-line decisions are recorded — the dispute does not reopen.
- A non-repudiable reconciliation record protects both sides.
Metric: dispute duration from denial to closure; share of lines closed without escalation.
Boundary: the panel does not decide who is right — it makes the evidence shared; decisions and signatures remain with the parties.
The panels are linked: the better binding conflicts are resolved, the fewer disputed lines reach the act. The cleaner the act, the fewer disputes with the insurer. The product is honestly built to unload itself over time — value shifts from resolving conflicts to preventing them.
See the panels on the demo stand.
10-minute demo